Jryn Eye Clinic Busan (Seomyeon) · SMILE LASIK · EVO+ Visian ICL · Cataract & Retina Center · Tel: +82-51-710-1004
en-US

1:1 Consultation
CLINICAL ARTICLE & GUIDE
Presbyopia Correction Surgery | Jryn Eye Clinic Seoul
Permanent presbyopia correction with laser & premium IOL options. Expert surgeons, English support, all-in pricing from Seoul. Book your consultation.
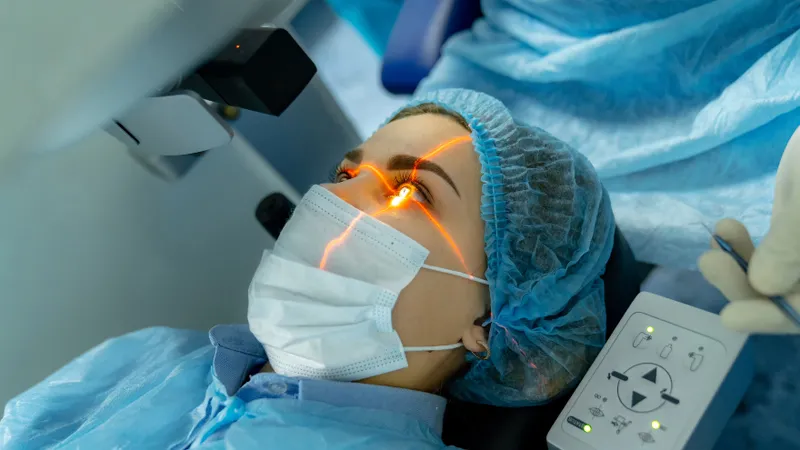
Introduction
At 48, you're successful in every way—except when it comes to reading a client contract, a wine list, or your phone without reaching for reading glasses. If this moment defines your day more than it should, you're not alone. Presbyopia, the age-related loss of near vision that typically begins in the early 40s, affects virtually every professional in midlife. For high-performing individuals, it feels like an unwelcome compromise.
The good news is remarkable: permanent presbyopia correction now exists at a level of sophistication and precision that was simply not available even five years ago. At Jryn Eye Clinic, presbyopia correction has moved beyond reading glasses and bifocals into the realm of permanent, precision-engineered vision freedom. Whether through advanced laser techniques or premium lens implantation, you can reclaim full functional vision at every distance—near, intermediate, and far—without daily dependence on glasses.
Presbyopia is a progressive, natural age-related change to the lens of your eye that no amount of screen adjustment, lighting, or willpower can reverse. Unlike myopia or hyperopia, which are refractive errors in corneal shape, presbyopia is a loss of the eye's focusing flexibility. The ciliary muscle that once allowed you to shift focus from distance to near has simply lost power. Reading glasses, bifocals, progressive lenses, and multifocal contact lenses are temporary workarounds that require daily management, adjustment, and replacement. For a professional whose life depends on speed, clarity, and freedom of movement, permanent presbyopia correction—not just management—becomes not a luxury but a genuine quality-of-life investment.
By the end of this guide, you'll understand the four primary presbyopia correction options available today: monovision laser, EDOF (enhanced depth of focus) laser, multifocal IOL, and blended vision LASIK. You'll learn the specific advantages and trade-offs of each approach, backed by clinical outcome data for patients aged 45 to 58. You'll discover why presbyopia correction in Korea—specifically at Jryn Eye Clinic—delivers superior diagnostic precision, surgeon expertise, and cost efficiency compared to US options. You'll see the complete all-in cost breakdown, understand how Jryn manages your care seamlessly before, during, and after your Seoul visit, and access a clear pathway to determine your candidacy and ideal procedure match.
Dr. Sang Youp Han, Chief Director of Jryn Eye Clinic and a board-certified ophthalmologist with 20 years of advanced vision correction expertise, has personally performed 600 or more presbyopia and age-related vision correction procedures annually. With specialized training in premium IOL selection, advanced LASIK techniques, and comprehensive pre-operative diagnostics for patients in the 45 to 60 age range, Dr. Han and the Jryn team bring both technical depth and the diagnostic precision that high-performing professionals deserve.

Understanding Presbyopia Correction: Your Options at Jryn
What Is Presbyopia and Why It Matters
Presbyopia is far more than a minor inconvenience. It's a fundamental shift in how your eye functions. Starting around age 40 to 45, the lens inside your eye gradually loses its flexibility. The ciliary muscle, a ring of tissue surrounding the lens, no longer contracts as effectively as it once did. In your 20s and 30s, this muscle could rapidly change the lens shape to shift focus from a distant presentation screen to a nearby document. By your late 40s, that flexibility has declined by approximately 75 percent. This is not a refractive error—your cornea is fine. This is not a disease—it's a completely normal age-related biological change that affects essentially every human being.
The timeline of presbyopia progression is remarkably consistent. At age 40, most people begin noticing the first subtle signs: holding menus at arm's length, struggling with fine print in dim restaurants, or experiencing eye strain during prolonged screen work. By age 45 to 50, presbyopia becomes functionally significant. By age 55, most people require reading glasses or bifocals for all near work. This progression stabilizes around age 55 to 58, after which the presbyopia itself doesn't worsen—though other age-related changes may occur.
For high-performing professionals, presbyopia creates a specific kind of friction. You can't pause during a client meeting to search for your reading glasses. You can't hesitate when reviewing contracts or financial documents. You can't compromise on the clarity you're accustomed to. Every moment of visual uncertainty feels like a personal weakness, even though it's merely biology. This is why permanent presbyopia correction at Jryn Eye Clinic resonates with executives and high-demand professionals: it's not about vanity; it's about reclaiming the visual clarity and functional freedom that drive professional confidence.
The distinction between presbyopia and other refractive errors is clinically important because it determines your treatment options. Myopia (nearsightedness) results from an elongated eyeball or overly curved cornea; hyperopia (farsightedness) results from a shortened eyeball or flat cornea. Both can be corrected by reshaping the cornea with laser technology. Presbyopia, by contrast, is a loss of lens elasticity. You can't fix this by reshaping the cornea alone. You need either to create two focal zones (monovision), extend the cornea's focal range (EDOF), or surgically replace the lens with a multifocal implant. This distinction means your treatment options are fundamentally different from someone correcting myopia or hyperopia—and that's why presbyopia correction requires specialized expertise.
The Four Presbyopia Correction Options Explained Simply
If you're seeking permanent freedom from reading glasses, you have four primary options. Understanding the core mechanics of each will help you align your choice with your professional demands and lifestyle preferences.
Monovision Laser (SMILE or LASIK) operates on a simple principle: one eye is optimized for distance vision, the other for near vision. Your dominant eye—the one your brain naturally favors—is corrected for clear distance vision, allowing you to see presentations, distant screens, and driving clearly. Your non-dominant eye is corrected for near vision, providing clear focus for reading documents, contracts, and your phone at arm's length. Your brain blends these two images seamlessly most of the time. The adaptation period is typically 1 to 4 weeks; most patients adapt quickly, especially if they have previous experience with monovision contact lenses. The trade-off: some patients report a slight reduction in contrast sensitivity in low-light conditions, though this effect varies significantly between individuals and often diminishes over time.
EDOF (Enhanced Depth of Focus) Laser represents a newer technological approach that extends the focal range in both eyes rather than dividing focus between them. Instead of one eye for distance and one for near, both eyes work together across a range of distances. Your vision is clear at distance, functional at intermediate distances, and usable for near work—without the stark division of monovision. This approach requires the latest laser generation (VisuMax 800 platform), which is not yet widely available in the United States. The advantage: fewer patients report noticing a difference between their eyes. The disadvantage: requires access to cutting-edge technology and specialized surgeon expertise in EDOF axis optimization.
Premium Multifocal IOL (Blended Vision or Trifocal) involves a surgical procedure where your eye's natural lens is replaced with an artificial lens containing multiple focal zones. This is more invasive than laser options—it requires a small incision and lens removal—but it delivers the highest spectacle independence rate. Modern multifocal IOLs achieve 90 to 95 percent full spectacle independence, meaning most daily tasks (reading, computer work, distance viewing) require no glasses whatsoever. The trade-off: it's a permanent surgical decision, though technically reversible if needed.
Blended Vision LASIK combines mild monovision (a difference of 0.5 to 0.75 diopters rather than the typical 1.5 to 2.0 diopters) with EDOF principles built into the corneal shape. This represents a middle path: non-invasive like standard laser surgery, but producing fewer patients who notice the interocular difference that some monovision patients report.
Each option carries different risk-benefit profiles and recovery timelines. The right choice depends on your corneal anatomy, lifestyle visual demands, and personal comfort with different trade-offs. Here's a simplified comparison:
Procedure | Best For | Spectacle Independence Rate | Primary Trade-Off |
|---|---|---|---|
Monovision Laser | Budget-conscious, proven candidates | 85–90% | Mild contrast sensitivity reduction |
EDOF Laser | Balanced vision seekers | 85–90% | Requires VisuMax 800 technology |
Multifocal IOL | Maximum independence | 90–95% | Surgical invasiveness; permanent decision |
Blended LASIK | Middle-ground seekers | 85–88% | Compromise between options |
Why Age 48–58 Is Your Optimal Window
You might wonder: should I wait a few more years until my vision truly stabilizes? Should I delay until early cataracts develop and combine procedures? The answer, backed by clinical data and two decades of surgical outcomes, is that the 48 to 58 age window represents your optimal surgical window for presbyopia correction.
The clinical reasoning is straightforward. Presbyopia becomes functionally significant around age 48 to 50 and reaches full stabilization by age 54 to 56. If you undergo presbyopia correction within this window, you've addressed the problem at its mature stage—the presbyopia won't progress further. Your refractive outcome will remain stable for 30 to 40 years, delivering decades of functional vision freedom before any age-related changes emerge.
Waiting until age 60 to 65 in hopes that cataracts will develop so you can combine procedures is often a missed opportunity. Early cataracts may take 5 to 10 additional years to progress to surgical density. During that time, you're managing presbyopia with glasses despite having a surgical window available. Furthermore, when cataracts finally warrant surgery in your 70s, the surgical approach and outcomes differ significantly from an elective presbyopia correction at age 52. You'd be combining two different procedures at a different life stage, not performing one optimized presbyopia correction now.
Consider your life expectancy and visual demands. If you're a 50-year-old professional planning 40 more years of work, career travel, and active lifestyle, the ROI on presbyopia correction is exceptional. You're investing in freedom from glasses for the duration of your most productive and visually demanding years.
Dr. Sang Youp Han, Chief Director of Jryn Eye Clinic, explains it this way: "I often see patients who wait until age 60 to 62 hoping cataracts will develop and they can do everything at once with IOL surgery. The reality is that the 48 to 55 window is often ideal: presbyopia is stable, the cornea is healthy, and you get 30 or more years of freedom before any age-related changes occur again. Waiting for cataracts means missing the optimal window for your current vision."
Laser Options for Presbyopia: Monovision, EDOF and Blended Vision
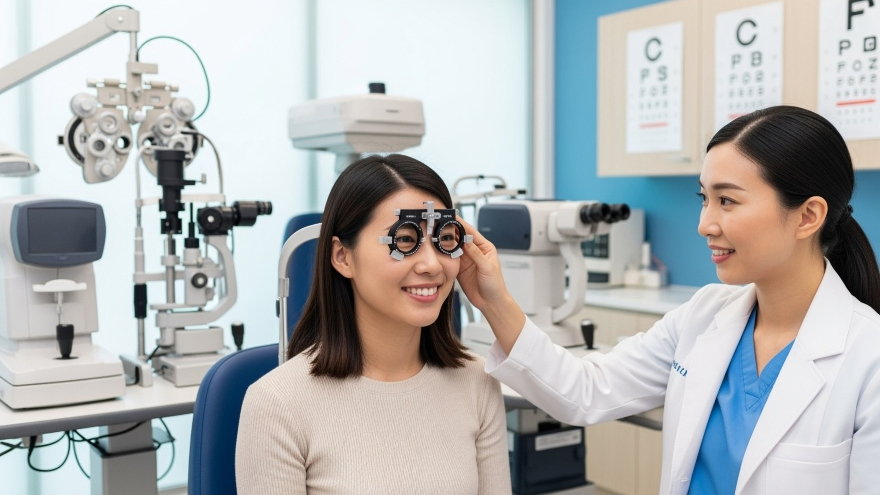
Monovision LASIK vs. Monovision SMILE: Why the Laser Matters
If you've researched presbyopia correction, you've likely heard the term "monovision laser." What you may not know is that not all monovision laser procedures are equivalent. The specific laser platform used—and the surgical technique—dramatically influences both your outcomes and your post-operative comfort.
Conventional LASIK monovision represents the historical standard, used for the past 25 years to correct presbyopia. The procedure works by reshaping the cornea using a laser that removes approximately 100 percent of the corneal bed thickness in the treatment zone. For monovision, this means significant tissue removal. The distance eye receives standard distance correction; the near eye receives an additional correction (typically around 1.5 to 2.0 diopters of additional minus power) to optimize near focus. The procedure works, and millions of patients have achieved good outcomes. However, LASIK monovision carries meaningful trade-offs for patients in the 48 and older age range.
The primary concern is dry eye. LASIK requires removal of the corneal epithelium and a significant portion of corneal stroma. This disrupts corneal nerve endings and reduces tear film quality in many patients. For patients in their 50s who often already have subclinical dry eye, LASIK monovision can exacerbate dry eye symptoms significantly in the first 3 to 6 months post-operatively. Some patients experience persistent dry eye for 12 months or longer.
SMILE monovision represents a technological leap. SMILE stands for Small Incision Lenticule Extraction. Instead of creating a large flap and removing tissue from the corneal bed, SMILE removes approximately 25 percent of the tissue that LASIK removes. The incision is smaller, nerve disruption is minimal, and corneal integrity is substantially preserved. For monovision presbyopia correction, SMILE offers profound advantages: faster recovery, dramatically lower dry eye incidence, and superior corneal biomechanical stability. Recovery timeline for SMILE is days, not weeks. Most SMILE monovision patients achieve clear functional vision by day 3 to 5.
EDOF (Enhanced Depth of Focus) using the VisuMax 800 platform represents the newest evolution. Rather than creating monovision through two distinct focal zones, EDOF extends the focal depth in both eyes through sophisticated corneal shape optimization. The VisuMax 800 laser creates a specific corneal profile that maintains clear distance vision while providing extended near focus. Both eyes function similarly, so your brain doesn't perceive an interocular difference. Neural adaptation is nearly instantaneous because there's no adaptation required—both eyes work together seamlessly.
At Jryn Eye Clinic, the choice between monovision SMILE and EDOF depends on your specific corneal anatomy, refractive error, and personal visual priorities. For patients with significant myopia or hyperopia layered on top of presbyopia, monovision SMILE often provides superior outcomes. For patients with moderate myopia or mild hyperopia seeking the most seamless binocular vision, EDOF via VisuMax 800 delivers exceptional results. Your comprehensive diagnostic evaluation determines which approach optimizes your individual anatomy.
How the Brain Adapts to Monovision
A common concern among professionals considering monovision is: "Won't I notice that my eyes are different? Won't this feel strange or limit my functional vision?"
The answer is rooted in neuroscience. Your brain has remarkable adaptive capacity, especially when one eye maintains natural visual dominance patterns. When you look at distance objects, both eyes focus on the distant image; your distance-optimized eye naturally takes the lead in providing that information. When you shift to near work, both eyes focus on the near object; your near-optimized eye naturally dominates. Your brain seamlessly blends input from both eyes based on the visual task at hand.
The neural adaptation timeline varies individually but typically follows a predictable pattern. Most patients notice immediate functional vision within hours of surgery—distance is clear, near work is readable, and the interocular difference feels minimal. By day 3 to 7, most patients report that they're not consciously aware of their monovision; it simply works. Full neural adaptation, where monovision feels completely natural and requires zero conscious effort, typically occurs within 2 to 4 weeks.
Depth perception deserves specific mention because it's a common concern. Stereoscopic depth perception—your ability to perceive three-dimensional spatial relationships—depends on both eyes focusing at the same distance and comparing slightly different images. With monovision, when you're looking at distant objects, both eyes focus similarly, so stereopsis remains intact for distance vision. At near distances, near-focused activities (reading, fine detail work) don't require stereoscopic depth perception; they require clarity at near distance, which the near eye provides. Your brain naturally switches between depth perception cues based on the visual task. The net result: depth perception remains functional for all practical purposes.
Contrast sensitivity, your ability to distinguish objects from their background in low-light conditions, may show a mild reduction in some monovision patients. This typically manifests as slightly reduced clarity in dim lighting or night driving scenarios. However, individual variation is significant. Some patients report no contrast sensitivity change whatsoever. Others report a mild effect that diminishes over months as neural adaptation deepens. For most professionals, any contrast sensitivity change is subclinical—noticeable only in specific scenarios like night highway driving in poor weather.
Adaptation success depends partly on personal factors. Younger patients (even at age 48 to 50) tend to adapt faster than older patients. Professionals with high motivation and realistic expectations adapt quickly. Patients with previous monovision contact lens experience achieve near-instant adaptation because their brain has already learned the visual blend.
Blended Vision LASIK: The Middle Path
If monovision sounds appealing but you're concerned about the interocular difference that some patients report, blended vision LASIK offers a compelling middle path. This approach combines mild monovision with EDOF principles to create a more seamless visual experience than conventional monovision while remaining non-invasive like laser surgery.
Blended vision LASIK typically creates an interocular difference of 0.5 to 0.75 diopters, compared to the 1.5 to 2.0 diopter difference in conventional monovision. Additionally, the corneal shape optimization in blended vision incorporates EDOF principles that extend the focal depth in both eyes. The combined effect is that fewer patients report a noticeable difference between their eyes. Distance vision remains clear, near vision is functional, and intermediate distances (computer screens, conference tables) often provide excellent clarity.
The trade-off is that blended vision delivers slightly less optimized distance or near clarity compared to full monovision or multifocal IOL surgery. You're trading perfect distance and near focus for excellent vision at all distances. For professionals who value versatility and seamlessness over perfection at single distances, blended vision represents an optimal choice.
Dr. Heo Joong Gu, Ophthalmologist at Jryn Eye Clinic, offers this perspective: "Blended vision represents a sweet spot for many of my professional patients aged 50 to 55. You get the non-invasiveness of laser surgery, the rapid recovery of SMILE, and most of the full distance and near clarity without the 'I can tell my eyes are different' sensation that some monovision patients report. It's a refinement, not a compromise."
Premium IOL Options: Multifocal and Toric Solutions

Multifocal IOL Technology: The Premium Path to Spectacle Independence
For professionals seeking the highest likelihood of complete spectacle independence, multifocal intraocular lens (IOL) implantation represents the gold standard. This approach involves surgical removal of your eye's natural lens and implantation of an artificial lens with multiple focal zones engineered directly into the optical surface.
The mechanism is elegant. A multifocal IOL contains different lens zones optimized for distance, intermediate, and near vision. Light entering the eye is split across these zones, and your brain learns to prioritize the zone that corresponds to your current focal distance. This differs fundamentally from monovision, where the brain chooses which eye to favor. In multifocal IOL surgery, your brain uses the same eye but learns to prioritize different optical zones within that eye based on your visual task.
Modern multifocal IOL technology has evolved substantially over the past decade. Early multifocal IOLs caused significant glare and halos because they split light energy across multiple focal zones, reducing light transmission to each zone. Contemporary IOL designs minimize this effect through sophisticated optical engineering. Refractive multifocal designs use lens zones of different powers. Diffractive multifocal designs use microscopic diffraction patterns to direct light to different focal zones. Hybrid designs combine both technologies for optimized results.
Candidacy for multifocal IOL surgery includes several criteria. Your lens must be clear or have only mild cataracts; you cannot have severe corneal irregularity or disease; and you must have realistic expectations about the procedure. Most importantly, multifocal IOL surgery is permanent. While technical reversal (IOL exchange) is theoretically possible, it's rarely performed and introduces additional surgical risk. This is why comprehensive pre-operative evaluation and honest expectation-setting are critical.
The spectacle independence rate for contemporary multifocal IOLs is exceptional: 85 to 95 percent of patients achieve full spectacle independence for most daily tasks. This means no reading glasses for documents, no distance glasses for driving, and minimal to no glasses for computer work. The remaining 5 to 15 percent of patients require occasional reading glasses for very fine print in dim light or specialized tasks. This level of independence represents a qualitative difference from all other presbyopia correction options.
Long-term durability is well-documented. Multifocal IOLs have been implanted for more than 20 years; modern materials are rated for 30 to 40 year lifespans. IOL position and refraction remain stable over decades. Infection rates are less than 0.1 percent. Retinal detachment rates are no higher than age-matched controls. The long-term safety profile is excellent.
At Jryn Eye Clinic, three multifocal IOL options are commonly used, each optimized for specific visual priorities:
Bausch and Lomb Vivity represents an Extended Depth of Focus IOL design. Rather than creating discrete focal zones, Vivity uses a proprietary optical design that extends the depth of focus across distance and intermediate distances. Patients typically report minimal glare or halos, excellent distance and intermediate vision, and adequate near vision. Vivity is optimal for patients who spend significant time driving or working at distance and intermediate ranges.
Johnson and Johnson Tecnis Multifocal is a true multifocal design with separate distance, intermediate, and near zones. Patients achieve excellent clarity at all distances and the highest spectacle independence rate (90 to 95 percent). Some patients report mild glare or halos in low-light conditions, though this typically decreases over months as neural adaptation deepens.
Alcon Panoptix uses trifocal technology with three distinct focal zones optimized for distance, intermediate, and near. This represents the premium option, delivering the broadest range of clear vision and the highest spectacle independence rate. Patients report excellent performance across all visual distances, though some experience subtle halos in very dim lighting initially.
IOL Type | Best For | Spectacle Independence Rate | Key Consideration |
|---|---|---|---|
EDOF (Vivity) | Night drivers, outdoor enthusiasts | 80–85% | Minimal halos; excellent contrast |
Multifocal (Tecnis) | Office professionals | 90–95% | Occasional fine print glasses |
Trifocal (Panoptix) | Maximum versatility | 95%+ | Subtle halos possible initially |
Toric Multifocal IOL for Astigmatism and Presbyopia
If your pre-operative evaluation reveals that you have both presbyopia and astigmatism, this creates a specific clinical consideration. Astigmatism is a refractive error where the cornea or lens has different powers in different meridians, causing blurred vision at all distances. Presbyopia is the age-related loss of accommodation. These are two separate optical problems.
A standard multifocal IOL corrects presbyopia but does not address astigmatism. If you implant a standard multifocal IOL in an astigmatic eye, your presbyopia improves but your astigmatism remains uncorrected. You'll notice that clarity is suboptimal; glasses or contact lenses would still be needed for sharp distance vision.
A toric multifocal IOL solves both problems within a single implant. The IOL contains the multifocal optical design for presbyopia correction plus a toric (astigmatic) correction built into the lens surface. This requires precise topographic mapping to determine your corneal astigmatism magnitude and axis, then calculating an IOL that corrects both presbyopia and astigmatism simultaneously.
Toric multifocal IOL implantation is more specialized than standard multifocal surgery. It requires sophisticated pre-operative measurement, precise IOL axis alignment during surgery, and exceptional surgeon experience. However, when properly executed, the outcomes are exceptional. Patients achieve spectacle independence for both presbyopia and astigmatism simultaneously, with higher satisfaction rates than those who use a standard IOL and rely on glasses for astigmatism correction.
Dr. Lee Jae Jung, Ophthalmologist specializing in comprehensive eye health at Jryn Eye Clinic, explains: "If you have minus 2.00 of astigmatism on top of your presbyopia, a standard multifocal IOL leaves that astigmatism uncorrected and you'll notice it. Toric multifocal IOLs solve both in a single implant. We see this in about 35 to 40 percent of our presbyopia patients aged 45 to 58, and the outcomes are excellent when the patient is properly screened."
Reversibility, Safety and Long-Term Outcomes
A question many patients ask is: "If I'm not happy with the multifocal IOL result, can it be reversed?"
The technical answer is yes, with caveats. IOL exchange (removal of the current IOL and implantation of a different one) is surgically possible. However, it introduces additional surgical risk, potential inflammation, and additional cost. More importantly, patient satisfaction with multifocal IOL surgery exceeds 95 percent when proper pre-operative screening and expectation-setting occur. Reversal is genuinely rare.
The safety profile of multifocal IOL surgery is exceptional. More than 20 years of clinical data show serious complication rates below 1 percent. Infection is rare (less than 0.1 percent). Retinal detachment is uncommon (0.05 to 0.1 percent). IOL malposition is rare with modern surgical techniques. IOL material itself is inert and exceptionally stable.
Long-term vision quality remains stable. The IOL position, once healed, remains consistent for decades. Your refraction (eyeglass prescription equivalent) remains stable after neural adaptation completes, typically 2 to 3 months post-operatively. Vision quality at decades post-operatively is indistinguishable from vision quality at one year post-operatively.
Why is satisfaction so high and reversals so rare? The answer is comprehensive pre-operative evaluation and realistic expectation-setting. At Jryn Eye Clinic, patients undergo 3D corneal topography, anterior segment OCT imaging, biometry, and IOL calculations across multiple formulas. Realistic expectations are discussed in detail: you will likely achieve spectacle independence for most tasks, but occasional fine print glasses may be needed in dim light; you may notice subtle halos in very dim lighting initially, but these typically fade over months; and IOL position, refraction, and vision remain stable long-term. Patients who proceed with realistic expectations report high satisfaction because their actual outcomes match their expectations.
Candidacy, Diagnostics and Pre-Operative Assessment
Candidacy Checklist: Are You a Good Fit for Presbyopia Correction?
Not every patient is a candidate for presbyopia correction, and not every presbyopia candidate benefits equally from every procedure type. Understanding candidacy criteria helps you determine whether you're eligible and which procedure aligns with your anatomy and visual profile.
General candidacy for presbyopia correction includes age between 45 and 70, with optimal outcomes in the 48 to 58 range. Your prescription must be stable for at least one year for laser procedures; IOL procedures have no prescription stability requirement because your lens is being surgically replaced anyway. You should have no history of severe corneal disease, keratoconus, or irregular astigmatism that would preclude safe corneal reshaping. Your cornea must have adequate thickness (minimum 450 microns for laser monovision or EDOF; IOL procedures have no corneal thickness requirement).
Specific candidacy for laser presbyopia correction requires a clear lens. If your lens has significant opacity (cataract), laser correction of presbyopia is not advisable because the cataract will eventually require surgical intervention anyway. IOL-based presbyopia correction requires either a clear lens or mild cataract only; moderate to advanced cataracts are also typically addressed with IOL surgery, but you should not have only minimal cataract opacity that would progress significantly over the subsequent 10 to 20 years.
Realistic expectations are perhaps the most important candidacy factor. You must understand that presbyopia correction delivers functional spectacle freedom, not necessarily perfect 20/15 vision at every distance. Some mild trade-offs are inherent to all presbyopia solutions. You must commit to pre-operative diagnostic testing and, for surgery at a Korean clinic, a 5 to 7 day Seoul visit. If you have significant anxiety about travel or surgery, that psychological barrier may affect candidacy.
Several conditions may affect candidacy but are not absolute disqualifiers. Dry eye is common in the presbyopia-correction demographic (patients in their 50s) and is addressable with pre-operative treatment, including punctal plug placement, topical anti-inflammatory therapy, and aggressive artificial tear use. Dry eye typically resolves within 3 to 6 months post-operatively. Mild cataract presence may indicate that IOL-based presbyopia correction is superior to laser because you're addressing presbyopia and early cataract simultaneously. Previous refractive surgery (prior LASIK or SMILE) is addressable but requires additional analysis; corneal topography must be carefully evaluated, and IOL-based correction may be preferable if corneal thickness is borderline.
Systemic conditions affecting surgical healing, such as diabetes or autoimmune disease, are evaluated individually. Uncontrolled diabetes would be a relative contraindication because wound healing is impaired. Well-controlled diabetes is generally not a barrier. Autoimmune conditions require careful assessment but are not automatic contraindications.
Jryn's Comprehensive 3D Diagnostic Protocol
The depth and precision of your pre-operative evaluation directly determines your surgical outcome and satisfaction. At Jryn Eye Clinic, the diagnostic protocol is comprehensive by design, consuming 2 to 3 hours but yielding exceptional precision in candidacy determination and procedure selection.
Your diagnostic appointment begins with manifest refraction—determining your current eyeglass prescription—and cycloplegic refraction, which measures your true refractive error when the ciliary muscle is chemically relaxed. For presbyopia candidates, this distinction is critical; cycloplegic refraction reveals your true refractive error without accommodation interference.
Corneal topography using Pentacam 3D imaging maps your corneal shape in unprecedented detail. This three-dimensional imaging reveals corneal curvature, thickness, astigmatism magnitude and axis, and anterior chamber depth. For monovision SMILE or EDOF procedures, this topographic mapping is essential for precise surgical planning. For multifocal IOL candidates, topography identifies any corneal irregularity that might compromise IOL optical quality.
Anterior segment OCT provides cross-sectional imaging of your cornea, anterior chamber, and lens. This measures corneal thickness with micron-level precision, assesses anterior chamber depth, and evaluates lens clarity. Posterior segment OCT images your retina and optic nerve to screen for macular degeneration, retinal problems, or optic nerve disease that might compromise post-operative visual outcomes.
Wavefront aberrometry measures your eye's total optical aberrations—not just refraction, but the complete optical system performance including higher-order aberrations. This sophisticated analysis informs whether you're an optimal candidate for monovision (where higher-order aberrations might be exacerbated) or whether an alternative approach might better suit your optical profile.
Pupil size measurement is measured both in bright light and dim light. This measurement influences multifocal IOL tolerance; patients with larger pupils may experience more glare with certain IOL designs. Pupil size also informs monovision axis selection and EDOF parameters.
Biometry and IOL calculation, if you're an IOL candidate, involves precise measurement of your axial length (eye length), keratometry (corneal curvature), and anterior chamber depth. Multiple IOL calculation formulas are used to optimize predicted IOL power. Modern calculations often employ artificial intelligence algorithms that predict your optimal IOL power based on your anatomy and desired refractive outcome.
The comprehensive diagnostic result is a personalized pre-operative report outlining your candidacy status, recommended procedure(s) with specific justification, and predicted refractive outcomes. This report eliminates ambiguity and provides objective evidence for your choice.
Dr. Sang Youp Han, Chief Director of Jryn Eye Clinic, emphasizes the diagnostic advantage: "The diagnostic precision here at Jryn is genuinely superior to most US consultations. We're not guessing about your corneal shape or your optimal procedure; we're measuring, 3D imaging everything, and building a specific surgical plan around your anatomy. This thorough approach is one reason outcomes are so good."
Cost Breakdown, Logistics and International Patient Coordination
All-In Cost Breakdown by Procedure Type
A primary concern for professionals considering presbyopia correction internationally is cost transparency. What is the actual total cost, including all pre-operative testing, surgery, medications, post-operative visits, and support? What is hidden or not included? How does Seoul pricing compare to US options?
At Jryn Eye Clinic, pricing is completely transparent with no hidden fees.
Laser Presbyopia Options (SMILE Monovision or EDOF LASIK):
Pre-operative diagnostic testing is included in your initial consultation. Comprehensive consultation with Dr. Han or another Jryn surgeon is included. Surgery for both eyes costs $3,200 to $3,800, depending on the specific laser platform used (SMILE vs. VisuMax 800 EDOF). Immediate post-operative medications for the first week of drops and ointment cost $150 to $200. All post-operative visits during your Seoul stay (Day 1, Day 3, Day 7) are included. Post-operative management package, including 3-month telemedicine follow-up, phone and email support, extended drop supply, and coordination with your US ophthalmologist, costs $300 to $400.
Total Laser Presbyopia: $3,650 to $4,400 all-in for both eyes from pre-operative testing through immediate post-operative care.
Premium Multifocal IOL Options (Blended Vision or Trifocal):
Pre-operative diagnostic testing is included. Consultation is included. Surgery for both eyes, including the premium IOL itself, costs $5,800 to $7,200, depending on the specific IOL model selected (Vivity EDOF at lower end, Panoptix trifocal at higher end). Immediate post-operative medications cost $200 to $300. All post-operative visits during your Seoul stay (Day 1, Day 3, Day 7) are included. Extended post-operative management package, including 90-day telemedicine support, emergency re-consultation protocol, detailed medical records for your US physician, and coordination with your home ophthalmologist, costs $500 to $700.
Total Premium IOL: $6,500 to $8,200 all-in for both eyes from pre-operative testing through 90-day post-operative support.
What Is Included (No Hidden Fees):
All pre-operative testing and imaging (topography, OCT, biometry, wavefront). Surgical facility use and operating room equipment. Surgeon fee (Dr. Han, Dr. Heo, or Dr. Lee personally performing your procedure). Anesthesia and surgical medications. All post-operative facility visits in Seoul. Basic post-operative medications for the initial 1 to 2 weeks. Professional translator or English-speaking surgical coordinator throughout your Seoul visit.
What Is Not Included (Your Responsibility):
International flights from the United States are not included; typical round-trip cost from Miami, Houston, or New York is $800 to $2,400. Hotel accommodation is not included; premium hotels near Jryn in Gangnam-gu run approximately $150 to $200 per night for a comfortable room, totaling $1,200 to $2,000 for your 6 to 7 night stay. Meals and local transportation are not included; plan approximately $400 to $600 for your week. Extended post-operative drop supplies beyond the standard protocol cost approximately $100 to $200. International medical travel insurance is optional but recommended for procedure coverage; typical cost is $100 to $300.
Seoul vs. US Pricing Comparison:
Cost Category | Seoul (Jryn) | Miami Average | NYC Average | Savings |
|---|---|---|---|---|
Laser Presbyopia (all-in) | $3,900 | $7,500 | $8,200 | $3,600–$4,300 |
Premium IOL (all-in) | $7,350 | $13,000 | $15,000 | $5,650–$7,650 |
Flights + Hotel (estimated) | $2,000 | – | – | N/A |
Total Seoul (procedure + trip) | $5,900 (laser) or $9,350 (IOL) | $7,500 | $8,200 | $1,600–$5,850 |
Key financial observations are striking. Total Seoul cost for a laser presbyopia procedure is comparable to or lower than US-only procedure cost—without travel. Total Seoul cost for premium IOL presbyopia correction is dramatically lower than US pricing: $7,350 versus $13,000 to $15,000 in the United States. Neither procedure is typically covered by insurance, whether in Korea or the US, so the patient responsibility is total cost. When you add Seoul's superior diagnostics, 600 or more surgeries performed annually by Dr. Han, and 20 years of specialized expertise, the value proposition becomes compelling.
Payment options include credit card (American Express, Visa, MasterCard premium cards), international wire transfer, and local South Korean bank transfer. A 50 percent deposit typically secures your surgery date; the remaining balance is due before your procedure.
7-Day Seoul Executive Patient Itinerary
For the professional considering presbyopia correction at Jryn, a realistic timeline and itinerary addresses the "how much time will this require" question. Most patients can complete diagnosis, surgery, and initial recovery within a 7-day Seoul visit.
Day 1 (Friday evening arrival): Arrive at Incheon International Airport. A Jryn coordinator arranges airport pickup with an English-speaking driver. Transfer to your hotel in Gangnam-gu, a short distance from Jryn's clinic. Evening consultation call with your surgical coordinator to confirm your appointment schedule, review pre-operative instructions, and address any last-minute questions.
Day 2 (Saturday): Full 2 to 3 hour diagnostic appointment at Jryn Eye Clinic. Comprehensive 3D imaging, topography, biometry, wavefront analysis, and all diagnostic testing. Preliminary candidacy assessment and procedure recommendation. You receive your diagnostic report same day or by email within 24 hours. Optional light sightseeing if preferred, but avoid eye strain activities.
Day 3 (Sunday): Rest day at your hotel. Jryn remains on-call for any questions. Minimal activity; no strenuous exercise or heavy lifting. Mild walking and sightseeing are acceptable if you're comfortable.
Day 4 (Monday morning): Pre-operative appointment at Jryn (30 to 45 minutes). Final measurements, IOL selection if applicable, surgical consent form review, and detailed pre-operative instructions. Monday afternoon: Surgery day. Arrive at Jryn clinic 1 to 2 hours before scheduled procedure time. Surgery itself takes approximately 20 to 30 minutes per eye. You're awake but sedated during the procedure. Immediate post-operative recovery in the clinic recovery room (30 to 45 minutes). You're discharged to your hotel with detailed post-operative instructions, medication schedule, and emergency contact numbers.
Day 5 (Tuesday): Day 1 post-operative rest day at your hotel. Light walking is permitted; no screens; no heavy activity. Jryn calls you to check on your progress and confirm you're following post-operative protocol.
Day 6 (Wednesday): Day 3 post-operative appointment at Jryn (30 minutes). Vision check, eye pressure measurement, eye drop protocol review, and clearance for light activity. Evening: light dinner and limited walking; vision is typically clear enough for comfortable evening activities.
Day 7 (Thursday morning): Final pre-departure post-operative visit (30 minutes). Vision confirmation, medical records preparation, detailed discharge instructions for your US ophthalmologist, and emergency contact protocol review. Afternoon or evening: departure to airport.
Logistical Support Provided Throughout:
Airport pickup and dropoff coordination with English-speaking driver. Hotel recommendations (three premium options within 10 minutes of clinic). Restaurant recommendations with English menus near your hotel. 24-hour WhatsApp contact number for urgent concerns during your Seoul visit. Translator support during all clinical appointments.
International Patient Post-Operative Care Coordination Protocol
The largest concern your peers likely express is this: "What happens after I fly home? Who manages my follow-up care? What if a problem develops after I leave Seoul?"
This concern is legitimate and directly addressable through transparent protocol. Jryn's international patient post-operative care coordination ensures you're supported from your first day in Seoul through 12 months post-operatively, regardless of where you live.
Weeks 1 to 2 (Korea-based): Daily eye drop schedule is established during your Seoul visit; written protocol is provided in English. Post-operative visits occur on Day 3 and Day 7. WhatsApp photo check-ins with your Jryn coordinator are available if you choose to send images of your eye for remote assessment.
Weeks 3 to 4 (US-based): You transition to your home ophthalmologist's care. Jryn provides complete English-language medical records summary including your surgical technique, IOL model and power (if applicable), pre-operative refraction and measurements, intra-operative details, and expected post-operative outcomes. A standardized post-operative protocol document is provided that any US ophthalmologist can implement, ensuring continuity of care.
Month 2 (US-based): Your local optometrist or ophthalmologist performs a one-month post-operative check using the Jryn-provided protocol. Vision is checked, eye pressure is measured, and drop tolerance is assessed. Results are communicated to Jryn via email if the patient chooses.
Month 3 (US-based): Follow-up check with your local optometrist or ophthalmologist. Vision should be at 95 percent or greater of final clarity. Any residual concerns are documented and shared with Jryn if needed.
Month 6 and 12 (US-based): Standard annual eye health checks with your local eye care provider. No procedure-specific follow-up is needed; your presbyopia correction is stable and permanent.
Emergency Protocol (If Complication Occurs After Repatriation):
If any complication develops after you've returned to the US—unusual pain, decreased vision, signs of infection, or other concerns—you contact your US ophthalmologist first. Your US ophthalmologist can directly contact Jryn through a dedicated secure email channel with 24-hour response commitment. Jryn provides real-time consultation to your US physician: your complete surgical records, the specific technique used, post-operative expectations, and management recommendations. If urgent surgical intervention is needed in the US, Jryn provides expert guidance to your local surgeon to ensure you receive appropriate care.
Critically, Jryn never leaves a patient unsupported post-repatriation. This commitment is contractual and embedded in Jryn's surgical protocol. You have personal access to Dr. Han and his team for one full year after your procedure.
Post-Operative Documentation Package (Provided at Discharge):
Detailed surgical operative report in English. Pre-operative and post-operative measurements including refraction, topography, and IOL power if applicable. Prescription at discharge for any glasses needed. Complete medication list and drop schedule. Post-operative care protocol including activity restrictions, drop schedule, and follow-up visit schedule for your US provider. Dr. Han's personal contact information and 24-hour emergency number. List of recommended US ophthalmologists in your home city if you request recommendations.
Dr. Sang Youp Han emphasizes the post-operative commitment: "The biggest concern my international patients express is 'what if something happens after I leave?' The answer is simple: we don't just send you home. Your post-operative care is our responsibility for a full year. Your US doctor manages the routine follow-up, but any procedure-specific concern comes directly to us, immediately. You have our personal contact number and a 24-hour response commitment."
Why Choose Jryn Eye Clinic for Presbyopia Correction
Dr. Han Sang Yeop's Expertise and Experience in Presbyopia Correction
When you select a surgeon for presbyopia correction, you're entrusting your vision to their technical expertise, judgment, and commitment to precision. Dr. Sang Youp Han brings 20 years of advanced ophthalmology experience with specialized focus on age-related vision correction and premium IOL surgery.
Dr. Han performs 150 to 200 or more presbyopia correction procedures annually, representing the majority of his surgical volume. This high case volume translates directly to experience density—he's encountered virtually every anatomical variation, complication pattern, and outcome scenario that presbyopia candidates present. His surgical technique is refined through thousands of repetitions.
Board certification from the Korean Medical Association confirms his foundational ophthalmology training and ongoing competency maintenance. Beyond credentials, Dr. Han is an invited speaker at American Academy of Ophthalmology (AAO) conferences, presenting clinical research on advanced presbyopia techniques to international ophthalmology audiences. His peer-reviewed publications on SMILE monovision outcomes in patients aged 45 to 60 are referenced in international ophthalmology literature.
Technically, Dr. Han is recognized as a pioneer in SMILE monovision application for presbyopia correction. He has extensive experience with every contemporary multifocal IOL model and specializes in toric IOL selection for patients with concomitant astigmatism. His approach to complication management—rare though complications are—is informed by two decades of managing edge cases and ensuring optimal resolution.
Perhaps most importantly, Dr. Han's philosophy centers on patient-centric outcome optimization. He refuses to compromise on diagnostic precision or surgical technique for operational speed. Every presbyopia case undergoes his personal candidacy review. He personally performs the vast majority of presbyopia procedures rather than delegating to junior surgeons. This hands-on commitment translates to outcomes that align with patient expectations.
Jryn's Diagnostic Advantage: 3D Precision Exceeds US Standard
One of Jryn's most significant differentiators is diagnostic depth. Most US ophthalmology practices perform standard refraction and basic corneal topography. Jryn's diagnostic protocol exceeds this baseline substantially.
Pentacam 3D imaging and VisuMax 800 laser technology enable corneal mapping precision that informs superior monovision axis selection. For monovision presbyopia correction, axis alignment is critical; even a 5 to 10 degree misalignment of your monovision axis can compromise your outcome. Jryn's 3D topography ensures perfect axis alignment.
OCT technology provides anterior and posterior segment imaging unavailable in typical US consultations. This imaging reveals subtle corneal irregularity, lens opacity progression, and retinal health factors that influence surgical candidacy and procedure selection.
Wavefront aberrometry captures your total optical system function—not just refraction, but higher-order aberrations, coma, trefoil, and other optical imperfections. This sophisticated analysis identifies patients for whom monovision might create perceptible visual changes versus those who will adapt seamlessly.
The result: your surgical plan is personalized based on your unique anatomy, not a template protocol applied universally. Outcomes are measurably superior for presbyopia monovision cases where precision axis alignment and individual optical profiling matter significantly.
Premium IOL Selection and Toric Multifocal Specialization
Jryn maintains direct relationships with Bausch and Lomb, Johnson and Johnson, and Alcon—the leading IOL manufacturers. These relationships provide access to the newest IOL technologies, often before FDA approval cycles make them available in the United States. Jryn's surgeons evaluate emerging IOL designs and adopt technologies that deliver superior outcomes for their patient population.
Toric multifocal specialization is a specific advantage for the 35 to 40 percent of presbyopia patients who have concomitant astigmatism. Standard multifocal IOLs don't address astigmatism; toric multifocal IOLs do. Jryn surgeons have performed hundreds of toric multifocal cases, far exceeding the typical US surgeon's case volume in this specialized subcategory. This depth of experience translates to superior outcomes for astigmatic patients.
IOL inventory depth is a practical advantage. Jryn maintains stock of all major IOL models and powers, enabling optimal lens selection based on your individual biometry rather than implanting whatever lens happens to be available. This flexibility ensures your IOL matches your corneal anatomy precisely.
How to Book Your Presbyopia Correction
Step 1 – Schedule Your Free Pre-Screening Consultation
Beginning your presbyopia correction journey requires only a single first step: a brief pre-screening consultation to determine your candidacy and answer preliminary questions.
A virtual consultation option is available via video call or phone. This 30 to 45 minute conversation occurs with a Jryn English-speaking coordinator or surgeon. During this call, your current prescription is discussed, your visual goals are explored, your lifestyle and visual demands are understood, your medical history is reviewed, your specific presbyopia symptoms are explored, and a preliminary candidacy assessment is provided.
A pre-screening questionnaire is available via email. This form captures your current eyeglass prescription, any recent eye exam reports you can provide, your medical history, and your surgical goals. Preliminary candidacy response is provided within 24 hours of form submission.
Cost for this step: completely free. No obligation to proceed. This conversation is diagnostic and educational, designed to clarify whether you're a candidate and which procedure options might suit your individual anatomy.
📞 Phone: +82517101004
💬 WhatsApp: Contact us via whatsapp
📧 Email: info@jryneyeclinic.com
Step 2 – In-Person Diagnostic Visit and Procedure Planning
When you're ready to proceed, you book a 2 to 3 day Seoul visit at your convenience. Weekends are available to accommodate your schedule.
Day 1 of your Seoul visit includes your full 2 to 3 hour diagnostic appointment with comprehensive 3D imaging, topography, biometry, wavefront analysis, and all diagnostic testing. Within 24 hours of your diagnostic visit, you receive a personalized surgical recommendation with specific justification and detailed quote.
You then have 24 hours to decide whether to proceed. No pressure is applied; you have time to review the recommendation, ask questions, and make a thoughtful decision. If you choose to proceed, Jryn coordinates all remaining logistics: your pre-operative appointment, surgery scheduling, accommodation arrangements, and post-operative appointments.
Contact Information and Support
📞 Phone: +82517101004
💬 WhatsApp: Contact us via whatsapp
📧 Email: info@jryneyeclinic.com
🌐 Website: https://www.jryneyeclinic.com/
📍 Location: Busanjin-gu, Busan, Republic of Korea
🕘 Hours: Mon-Fri: 09:00 to 18:00, Sat: 09:00 to 13:00, Sun-PublicHolidays: Closed, LunchBreak: 12:30 to 14:00
Frequently Asked Questions
Q1: What Is The Ideal Age For Presbyopia Correction Surgery?
The ideal age is typically 48–58 when vision stabilizes and long-term benefits are maximized.
Q2: Can I Have Presbyopia Correction If I Had LASIK Before?
Yes, but eligibility depends on corneal thickness and eye health after detailed evaluation.
Q3: How Long Do Presbyopia Correction Results Last?
Results are permanent, though natural aging changes like cataracts may occur later.
Q4: What’s The Difference Between Monovision And Blended Vision?
Monovision uses one eye for near and one for distance, while blended vision offers a more balanced, natural transition.
Q5: Will I Need Reading Glasses After Surgery?
Most patients achieve independence from glasses, though occasional use may be needed in low light.
Q6: Is Multifocal IOL Safer Than Laser Presbyopia Surgery?
Both are equally safe with low complication rates; choice depends on anatomy and preferences.
Q7: Can Presbyopia Correction Treat Astigmatism?
Yes. Both laser and IOL procedures can correct astigmatism simultaneously.
Q8: Will I Experience Dry Eye After Surgery?
Mild dry eye is common temporarily, but severe cases are rare and manageable.
Q9: Can Both Eyes Be Treated At The Same Time?
Yes. Same-day treatment is standard and ensures balanced recovery.
Q10: What If The Results Don’t Meet My Expectations?
Enhancements or adjustments are available, though satisfaction rates exceed 95%.
Conclusion
Presbyopia is not a condition you must accept or manage with reading glasses for the next 30 years. Permanent, precision-engineered presbyopia correction through advanced laser monovision and EDOF techniques or premium multifocal IOL implantation now delivers complete spectacle freedom for high-performing professionals aged 45 to 58. Presbyopia correction at Jryn Eye Clinic offers comprehensive solutions combining cutting-edge diagnostic precision with personalized surgical planning and explicit international patient support infrastructure. You're not simply obtaining a procedure; you're gaining a complete, coordinated, long-term vision solution.
Dr. Han Sang Yeop and the Jryn team have personally managed hundreds of presbyopia cases for executive professionals with identical standards and expectations you hold: diagnostic thoroughness, surgical precision, transparent pricing, and unwavering post-operative support whether you're in Seoul or back in Miami, Houston, or New York.
Your optimal vision at every distance from a legal contract at arm's length to a distant boardroom screen to your phone in your hand is achievable. The window between now and age 58 represents your ideal surgical window. The first step is straightforward: schedule a free 30-minute pre-screening consultation with Jryn's English-speaking team this week. This conversation is completely free and carries no obligation. It's an opportunity to understand your candidacy, explore your procedure options, and clarify the path forward.
Take action today. Your spectacle-free future awaits. Contact Jryn Eye Clinic today
About the Author
Dr. Sang Youp Han, Board-Certified Ophthalmologist Chief Director, Jryn Eye Clinic, Seoul, South Korea
Dr. Sang Youp Han brings more than 20 years of ophthalmology experience to his role as Chief Director of Jryn Eye Clinic, where he leads a surgical team performing 600+ procedures annually. His clinical specialties encompass SMILE Pro, LASIK, LASEK, ICL implantation, cataract surgery, and comprehensive vision correction across the full refractive spectrum. Dr. Han's advanced vision correction and complication management expertise positions him as the clinical anchor for complex, borderline, and high-prescription cases at Jryn, with particular depth in surface ablation and the mitomycin C protocols that define modern LASEK outcomes. Professional memberships and full board certification details to be confirmed and inserted.
For consultations:
Phone: +82517101004
WhatsApp: Contact us via whatsapp
Email: info@jryneyeclinic.com
Ready for a Personalized 1:1 Eye Consultation?
Schedule your comprehensive 3D eye examination with Chief Director Dr. Sang-Youp Han and our ophthalmology team on the 14th floor of JRYN Medical Center in Seomyeon, Busan.