Jryn Eye Clinic Busan (Seomyeon) · SMILE LASIK · EVO+ Visian ICL · Cataract & Retina Center · Tel: +82-51-710-1004
en-US

1:1 Consultation
CLINICAL ARTICLE & GUIDE
Advanced Cross-Linking for Keratoconus in Busan
Advanced cross-linking for keratoconus in Busan: modern CXL options, benefits, and what to expect. Protect your vision—book a consultation today.
Introduction
Keratoconus rarely begins with alarm. For many patients in Busan, it starts quietly—letters that seem slightly shadowed, night lights that blur more than they used to, glasses that stop working sooner than expected. At first, it feels manageable, even ignorable. In a city where long hours, heavy screen use, and dry eyes are part of daily life, vision changes are easy to blame on fatigue.
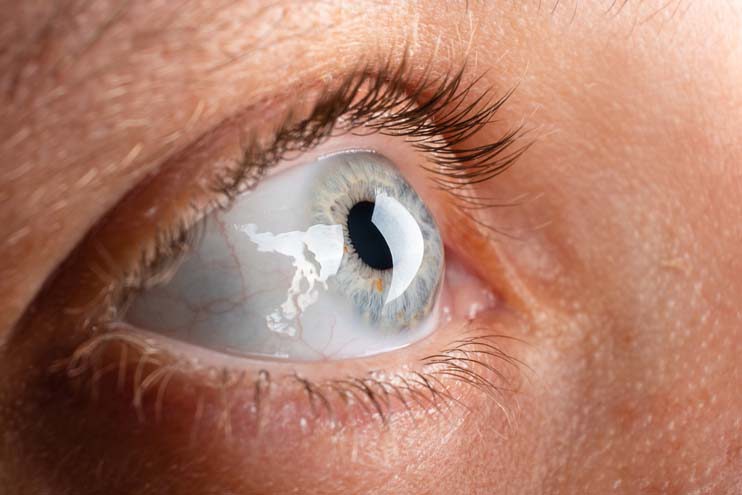
But keratoconus is not ordinary eye strain. It is a progressive corneal disease, one that weakens the structure of the eye itself. As the cornea thins and gradually changes shape, vision becomes increasingly distorted and unstable. Left unchecked, keratoconus can significantly limit visual function and, in advanced cases, threaten long-term eye health.
Over the past decade, however, the outlook for keratoconus patients has changed. Corneal collagen cross-linking (CXL) has shifted treatment from passive observation to active prevention of progression. More recently, advanced cross-linking techniques have made it possible to treat a wider range of patients—those with thinner corneas, faster progression, or complex clinical profiles—more safely and effectively.
At Jryn Eye Clinic in Busanjin-gu, keratoconus is not treated as a one-time diagnosis, but as a long-term condition requiring precision, timing, and individualized care. This article explains what advanced cross-linking really means, who benefits most from it, and why early, thoughtful intervention can make a lasting difference in preserving vision.
Understanding Keratoconus Beyond the Textbook
From a medical perspective, keratoconus involves progressive thinning and biomechanical weakening of the corneal tissue. From a patient’s perspective, it feels like vision that refuses to settle.
You may notice:
Increasing astigmatism that glasses cannot fully correct
Ghosting or double images, especially with white text on dark backgrounds
Glare and starbursts around lights
Frequent prescription changes
Growing dependence on rigid or specialty contact lenses
What people often overlook is that keratoconus progression is not always obvious subjectively. Some patients adapt surprisingly well, compensating unconsciously by squinting, holding screens closer, or avoiding night driving. Meanwhile, corneal maps tell a different story.
This is why modern keratoconus care depends less on “how blurry you feel” and more on objective measurements over time.
The Core Goal of Cross-Linking: Stability, Not Perfection
Corneal cross-linking works by strengthening the cornea’s collagen fibers. Riboflavin (vitamin B2) is applied to the cornea and activated by ultraviolet-A light, triggering chemical bonds that increase corneal rigidity. The concept is simple: reinforce the cornea so it can resist further deformation.
It’s important to be honest about expectations.
Cross-linking is not primarily designed to:
Restore perfect vision
Eliminate glasses or contact lenses
Reshape the cornea into an ideal form
Instead, its primary purpose is to halt or significantly slow progression. Any visual improvement that follows is a secondary benefit, not the main objective.
From a long-term perspective, stabilization is powerful. Stopping progression early can:
Preserve usable vision for decades
Maintain contact lens tolerance
Reduce the likelihood of corneal transplantation later in life
Standard Cross-Linking and Why “Advanced” Approaches Exist

The traditional foundation of cross-linking is often referred to as the Dresden protocol. This involves removing the corneal epithelium, saturating the cornea with riboflavin, and applying UVA light for a fixed duration. It has a strong safety record and remains an important reference point worldwide.
So why has the conversation shifted toward “advanced” cross-linking?
Because real patients do not come with identical corneas.
In actual clinical practice, ophthalmologists must manage:
Very thin corneas
Rapid progression in teenagers
Coexisting dry eye disease
Allergic eye rubbing habits
Occupational or lifestyle constraints
Anxiety about pain and recovery
Advanced cross-linking is not one single technique. It is a framework of customization, adjusting parameters to match the patient rather than forcing the patient to match the protocol.
Advanced Cross-Linking Techniques in Real Clinical Use
Accelerated Cross-Linking
Accelerated cross-linking delivers the same total energy in a shorter time by increasing light intensity. For patients, this often means:
Shorter procedure time
Reduced discomfort from prolonged exposure
Greater convenience for busy schedules
Clinically, the key question is not speed but appropriateness. Accelerated protocols are selected based on corneal thickness, cone location, and progression pattern.
Managing Thin Corneas Safely
One of the most stressful moments for keratoconus patients is being told their cornea is “too thin.” In the past, this could exclude patients from treatment.
Today, modified approaches allow cross-linking in thinner corneas by:
Using specialized riboflavin solutions
Monitoring corneal thickness closely during the procedure
Adjusting energy delivery to maintain safety margins
This is an area where experience matters. Thin-cornea cross-linking requires careful planning and real-time decision-making, not rigid formulas.
Epithelium-Off vs. Epithelium-On Approaches
Most established evidence supports epithelium-off (epi-off) cross-linking, where the surface layer is removed to ensure proper riboflavin penetration. This method is associated with:
More predictable strengthening
A few days of postoperative discomfort
Temporary vision fluctuation during healing
Epithelium-on (epi-on) techniques aim to reduce pain and speed recovery by leaving the surface intact. While newer developments are promising, results can be more variable depending on corneal permeability and protocol design.
From a clinic standpoint, the choice is not ideological. It is practical. The priority is achieving meaningful stabilization while maintaining safety.
Diagnosis Comes Before Treatment: Why Repeated Imaging Matters
One of the most common misconceptions is that keratoconus can be diagnosed—or ruled out—with a single scan.
In reality, progression is defined by change over time.
At Jryn Eye Clinic, evaluation typically includes:
Corneal topography and tomography
Thickness mapping (pachymetry)
Assessment of tear film stability
Review of eye rubbing and allergy history
Dry eye, which is common in Korea due to indoor heating, air conditioning, and screen use, can distort corneal measurements. Treating the ocular surface before making major decisions is often essential.
A careful diagnostic phase prevents two major mistakes:
Treating too late, after avoidable damage has occurred
Treating unnecessarily, when the cornea is stable
What Patients Actually Experience During and After Cross-Linking
Patients deserve clarity, not reassurance without context.
During the procedure:
The eye is numbed with drops
You will see bright light
You may feel pressure, but not sharp pain
After epi-off cross-linking:
Expect burning, tearing, and foreign body sensation for several days
Vision is typically blurry during epithelial healing
Light sensitivity is common in the first week
Recovery is gradual. Visual quality stabilizes over weeks to months, and contact lens refitting is often planned after healing is complete.
This is not a cosmetic procedure. It is a medical intervention with real recovery, but also real long-term benefit.
Life After Cross-Linking: What Changes and What Doesn’t
Many patients ask whether cross-linking means they can stop worrying.
The answer is nuanced.
After successful stabilization:
Progression risk is greatly reduced
Vision correction becomes more predictable
Long-term planning becomes possible
However:
Glasses or contact lenses are often still needed
Regular follow-up remains important
Eye rubbing must be actively avoided
Cross-linking changes the trajectory of keratoconus, not the fact that you have it.
What Defines a High-Quality Keratoconus Program in Busan
When choosing where to undergo cross-linking, look beyond equipment lists.
A strong program emphasizes:
Consistent, repeatable diagnostics
Clear criteria for progression
Experience with thin and complex corneas
Long-term follow-up planning
At Jryn Eye Clinic, keratoconus care reflects our broader philosophy: precision, patience, and personalization. Dr. Han Sang Yeop’s decades of experience guide decisions that prioritize long-term vision health over short-term convenience.
Conclusion
Keratoconus is a condition that unfolds over time, and the decisions made early often shape visual outcomes years later. While glasses and contact lenses may help manage symptoms, they do not address the underlying structural weakness of the cornea. Corneal cross-linking exists to change that trajectory, reinforcing the cornea and reducing the risk of continued progression.
Advanced cross-linking is not about using the newest technique for its own sake. It is about matching the right approach to the right cornea—considering thickness, progression speed, lifestyle, and long-term visual needs. For many patients, especially younger individuals, timely cross-linking can preserve vision stability, maintain contact lens tolerance, and reduce the likelihood of more invasive procedures in the future.
At Jryn Eye Clinic, keratoconus care reflects a broader commitment to precision-driven, patient-centered ophthalmology. Under the guidance of Dr. Han Sang Yeop, each treatment plan is built on careful diagnostics, realistic counseling, and respect for the fact that keratoconus management is a long-term partnership—not a single procedure.
Ready for a Personalized 1:1 Eye Consultation?
Schedule your comprehensive 3D eye examination with Chief Director Dr. Sang-Youp Han and our ophthalmology team on the 14th floor of JRYN Medical Center in Seomyeon, Busan.